
Special tests library › Low back & pelvis
Passive lumbar extension test
For: Lumbar segmental instability
Excessive or poorly controlled movement at one level of the lumbar spine, thought to provoke pain during movement, for example a painful catch on bending.
Treat with caution (see below)Short answer: Treat results with caution when testing for lumbar segmental instability: read the notes below before relying on one. In the source cited below, sensitivity was 84% and specificity 90%.
How it is done
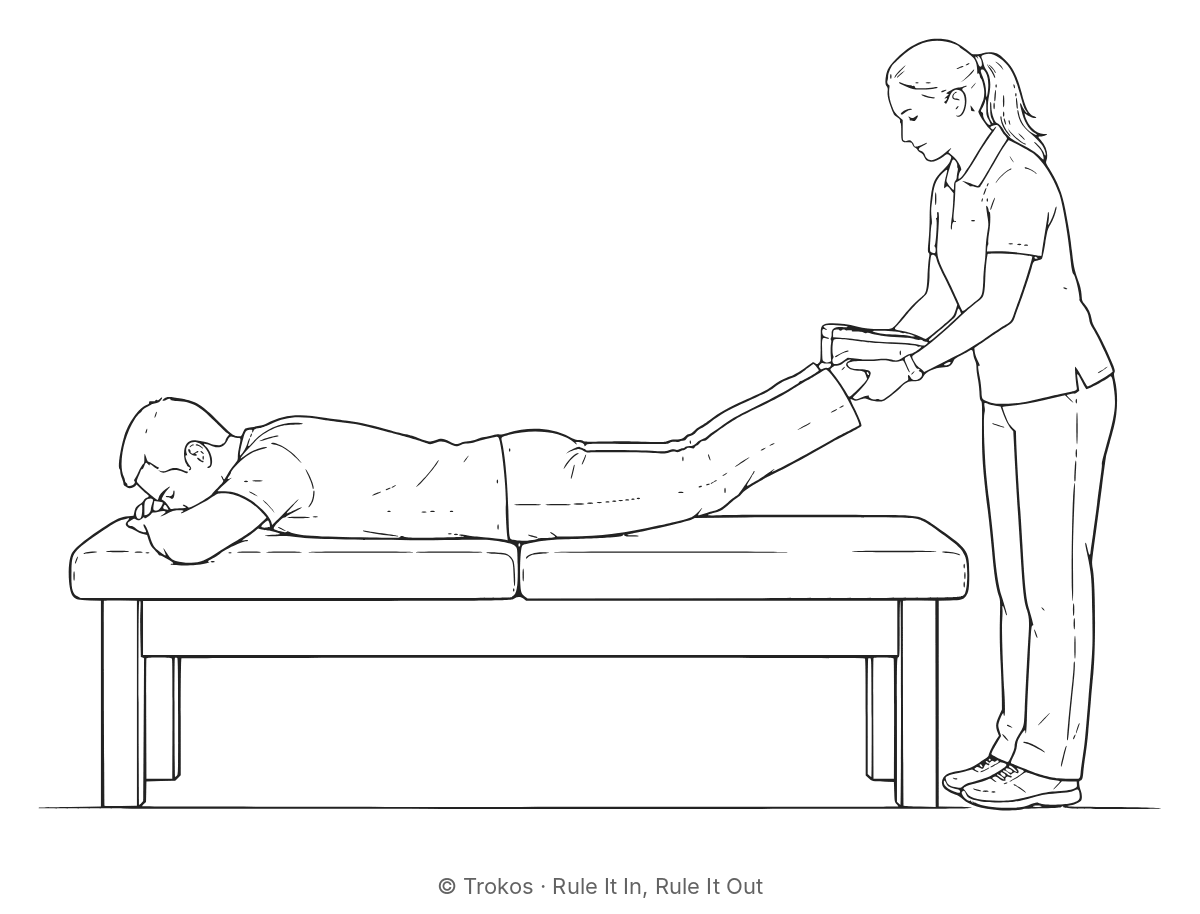
The patient lies prone. The examiner lifts both straightened legs together about 30 cm off the plinth with gentle traction, then lowers them. Positive: Low back pain, heaviness or a feeling of giving way during the lift that eases when the legs are lowered.
What the numbers mean
- Positive result: see the caution above before relying on this result.
- Negative result: see the caution above before relying on this result.
The ladder: what a result does to your estimate
| If you thought | After a positive | After a negative |
|---|---|---|
| 10% | 50% | 2% |
| 30% | 79% | 7% |
| 50% | 90% | 15% |
Calculated from the likelihood ratios above, as in the book. Read the caution above before relying on these. For any other starting estimate, use the probability calculator.
Work out what a result means for your patient: probability calculator
How common is it? Starting probabilities by setting
Red flags to screen for before testing the low back & pelvis
LR+ 8.84 as published by the authors (from sensitivity 84.2% and specificity 90.4%); LR− 0.17 calculated from those figures. Sensitivity and specificity shown rounded. Reference standard: instability on flexion–extension radiographs. Checked against the full paper on 15 October 2026.
Its negative likelihood ratio reaches the usual rule-out threshold, but the book does not count it as a reliable rule-out test.
Caution: A smaller study in surgical patients (Esmailiejah 2018, 52 patients, instability judged at operation) found lower sensitivity (79%), so a negative result may not rule instability out.
Do two examiners agree?
Moderate to substantial (kappa 0.46-0.76; 70 patients, 2 studies) (abstract source only for Rabin 2013). Source: Rabin 2013; Alyazedi 2015.
Rule It In, Rule It Out gives the full reliability detail: every study, the same examiner versus two examiners, and the patients tested.
Study details: patients, setting, confidence intervals, what was read
| Study | Kasai 2006 (prospective diagnostic accuracy study) |
|---|---|
| Patients | 122 patients; consecutive patients at a university hospital spine clinic in Japan with lumbar degenerative disease (89 spinal stenosis, 21 spondylolisthesis, 12 degenerative scoliosis; mean age 69); many referred for surgical opinion, 37% had surgery within a year; 38 had instability, 84 did not |
| Compared against | instability on flexion–extension X-rays (angular motion 20° or more, translation 5 mm or more, or end-plate angle −5° or less on the flexion film; measured by two orthopaedists, 100% agreement) |
| 95% confidence intervals | sensitivity 70–93%, specificity 82–95% (calculated from the study’s counts) |
| Counts | true positives 32, false positives 8, false negatives 6, true negatives 76 |
| Likelihood ratios | published LR+ (8.84, 95% CI 4.51–17.33); LR− calculated |
| What we read | Full paper (Phys Ther 2006;86:1661–1667, via EBSCO PDF), Table 2 (counts 32/6/8/76) and Table 3 (sensitivity 84.2%, specificity 90.4%, LR+ 8.84, 95% CI 4.51–17.33). No LR− or sensitivity/specificity CIs published. Specificity from the counts is 76/84 = 90.5%; the paper prints 90.4%. |
| Things to bear in mind | Well run for its size: consecutive patients, two examiners who did not know the X-ray result, and the test repeated at a second visit with the same result every time. But it was a surgical referral clinic with fairly severe disease and a high rate of instability (31%), so the test may look better than in a general clinic, as the authors note; only 38 had instability, and the X-ray cut-offs used as the reference standard were chosen by the authors without an agreed standard. |
How these details are gathered and checked: Methods.
Source
Kasai Y, Morishita K, Kawakita E, Kondo T, Uchida A. A new evaluation method for lumbar spinal instability: passive lumbar extension test. Phys Ther. 2006;86(12):1661–1667. PubMed · single study
Also cited: Esmailiejah AA, Abbasian M, Bidar R, Esmailiejah N, Safdari F, Amirjamshidi A. Diagnostic efficacy of clinical tests for lumbar spinal instability. Surg Neurol Int. 2018;9:17. Journal article (DOI)
Figures as they will appear in Rule It In, Rule It Out (Trokos, forthcoming). If a newer or better study changes them, this page changes with the book. Figures last updated from the book on 13 October 2026.
How to cite
Citing a figure? Cite the study it comes from. The main figures on this page come from:
Kasai Y, Morishita K, Kawakita E, Kondo T, Uchida A. A new evaluation method for lumbar spinal instability: passive lumbar extension test. Phys Ther. 2006;86(12):1661–1667.
Figures quoted in the notes from other studies are cited under Source above.
Citing this page as a summary:
APA 7: Tompson, S. (2026, October 13). Passive lumbar extension test for lumbar segmental instability. Trokos special tests library. Retrieved October 28, 2026, from https://trokos.com.au/tests/lumbar-ple.html
Vancouver: Tompson S. Passive lumbar extension test for lumbar segmental instability [Internet]. Sunshine Coast (QLD): Trokos; 2026 [updated 2026 Oct 13; cited 2026 Oct 28]. Available from: https://trokos.com.au/tests/lumbar-ple.html
Citing the whole library:
APA 7: Tompson, S. (2026). Trokos special tests library (Version November 2026) [Online reference library]. Zenodo. https://doi.org/10.5281/zenodo.23932041
Vancouver: Tompson S. Trokos special tests library [Internet]. Version November 2026. Geneva: Zenodo; 2026 [cited 2026 Nov 4]. Available from: https://doi.org/10.5281/zenodo.23932041

Get the book for telling radicular leg pain from referred pain, and knowing when cauda equina means send now
This page gives the published figures. Rule It In, Rule It Out adds captioned drawings with the exact positions, the Rule-In / Rule-Out bar and evidence dots, a fuller interpretation of each test, and the clinical reasoning on which tests to use and in what order.
Look inside the book: free sample pages
Coming November 2026: 330 pages, paperback and PDF. Launch offer: subscribers get the PDF for A$39 instead of A$49, for the first two weeks after publication. Be first to know at launch
One study, one test, once a month
Rule It In is a free evidence letter for musculoskeletal clinicians: one recent study explained, one examination test with its real numbers. From Trokos, publisher of Rule It In, Rule It Out.
Free when you confirm your email: a one-page PDF of the strongest special tests to rule in and rule out, with tests that carry a caution flagged separately.
Launch offer for subscribers: the PDF edition of Rule It In, Rule It Out for A$39 instead of A$49, for the first two weeks after publication. Sign up free to get the code on launch day.
By subscribing you agree to receive Rule It In by email, about once a month. You will get a confirmation email first, and nothing is sent until you click it. Your address is stored by Kit (Kit.com, United States) and used only for this newsletter and the subscriber launch offer; Kit records which issues are opened and which links are clicked. Unsubscribe with one click in any issue. Privacy.